
Provider Referral Form
Isabel Hope Harbor Transitional Living
This referral form is for case managers, hospitals, treatment providers, probation/parole officers, courts, veteran organizations, and other service providers referring adult men age 21 and older for structured transitional living.
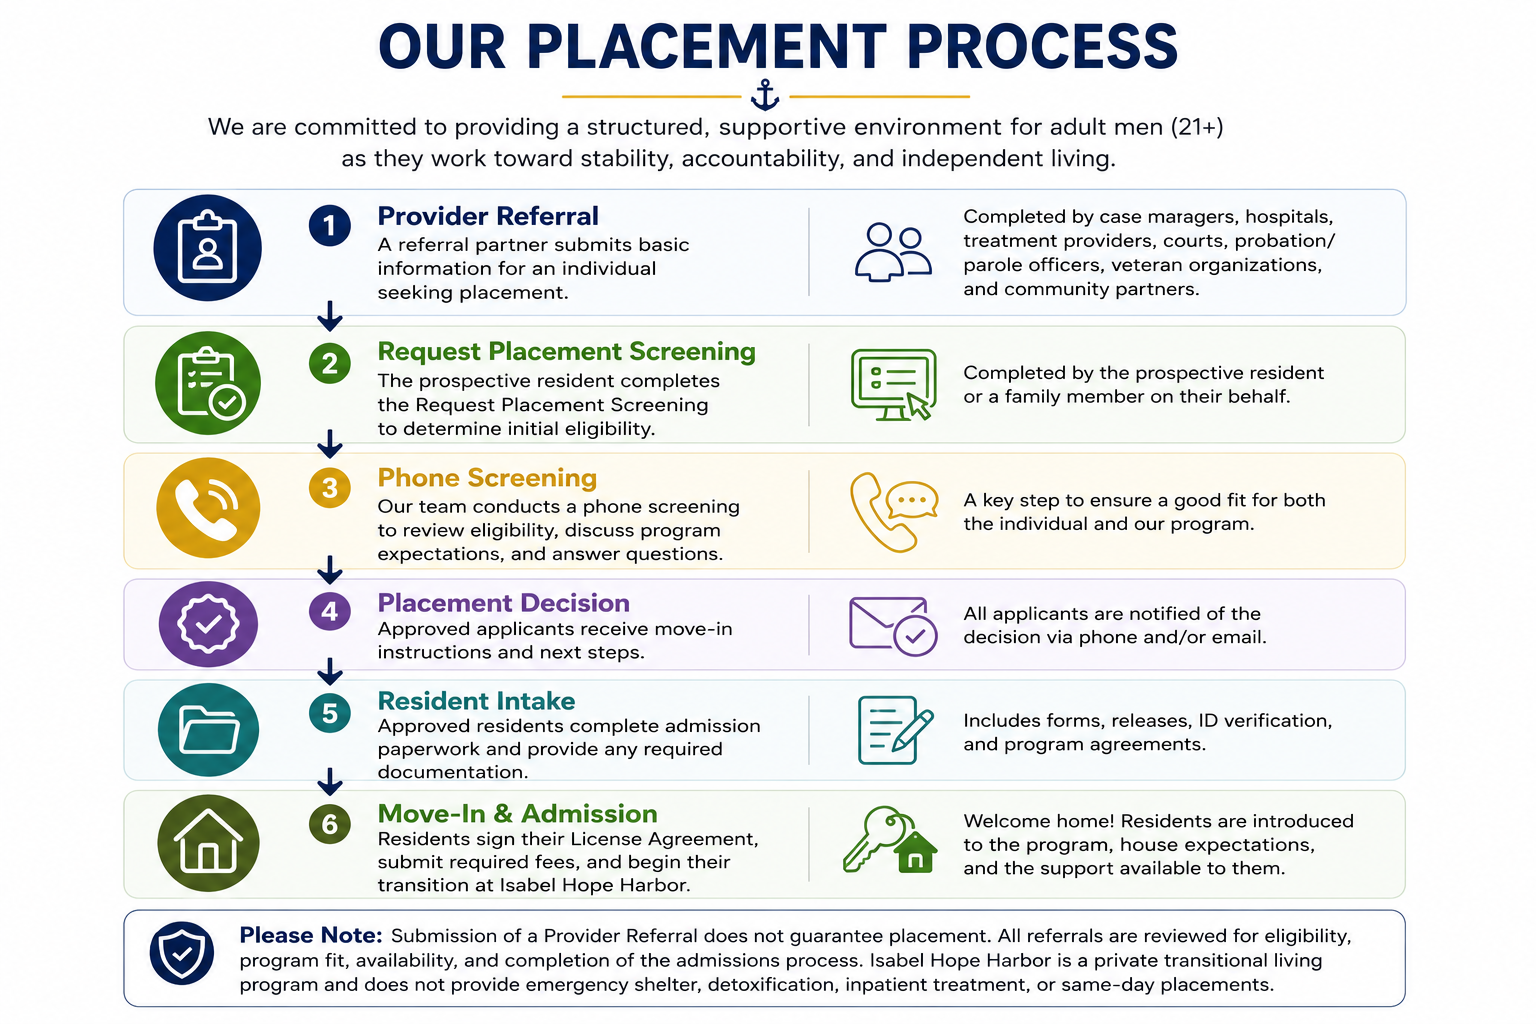
Submission of this referral is a request for placement review only and does not guarantee admission.
Isabel Hope Harbor is a private, non-clinical transitional living program. We do not provide emergency shelter, crisis housing, detoxification, inpatient treatment, or same-day placement.
Estimated Completion Time: 3–5 minutes
Section 1 – Referral Source
Organization Name: Text field
Referring Staff Name: Text field
Job Title: Text field
Phone Number: Phone field
Email Address: Email field
Referral Date: Date
Section 2 – Individual Information
Individual's Full Name: Client first nameClient last name
Date of Birth: Client birthdate
Phone Number (if available): Client phone
Is theIndividual is 21 years of age or older? Dropdown
Section 3 – Eligibility Screening
Is the individual male?
Dropdown
Is the individual clinically stable and appropriate for a non-clinical transitional living environment? Dropdown
Is the individual sober or willing to maintain a drug- and alcohol-free living environment? Dropdown
Is the individual willing to comply with house rules, curfew, random drug screening, and participate in a structured living environment? Dropdown
Is the individual required to register as a sex offender? Dropdown
Section 4 – Placement Information
Current Living Situation: Dropdown
Please provide additional details (optional): Paragraph
Desired Move-In Timeframe
○ Within 7 Days
○ Within 14 Days
○ Within 30 Days
○ Future Planning (30+ Days)
Section 5 – Phone & Communication
Does the individual currently have a working cell phone capable of making and receiving calls and text messages?
Dropdown
If No, is a phone expected prior to move-in?
Dropdown
A working cell phone is required for participation in Isabel Hope Harbor, including daily One Step check-ins and communication with staff.
Section 6 – Funding & Program Fee Acknowledgment
Primary Funding Source
○ Self-Pay
○ Family Support
○ Employer
○ Government Program
○ Veteran Benefit
○ Community Organization
○ Other
Has funding been verified?
○ Yes
○ No
○ Pending
Has the individual (or responsible party) been informed of Isabel Hope Harbor's program costs?
○ Yes
○ No
Funding has been confirmed for:
☐ $600 Shared (2 Men) - $800 Private (When Available) Monthly Program Fee
☐ $200 One-Time Move-In Fee
☐ Both
☐ Funding Pending
Current Program Costs
• Monthly Program Fee: $800
• One-Time Move-In Fee: $200
• Total Due at Move-In: $1,000 (unless alternative arrangements have been approved in advance).
Proof of funding is required prior to placement consideration.
Section 7 – Referral Notes
Please provide any information that will assist in determining whether the individual is an appropriate fit for Isabel Hope Harbor.
Examples include:
Recovery supports
Employment status
Case management involvement
Probation or parole supervision
Medical or mobility considerations
Transportation
Veteran status
Additional comments:Paragraph
Provider Acknowledgment
Checkboxes I certify that the information provided is accurate to the best of my knowledge.
☐ I understand this referral is a request for placement review only and does not guarantee admission.
☐ I understand Isabel Hope Harbor is not an emergency shelter, crisis housing program, detoxification center, inpatient treatment program, or state-funded halfway house.
☐ I understand all prospective residents must successfully complete Isabel Hope Harbor's screening and approval process before admission.
Thank You
Thank you for partnering with Isabel Hope Harbor to help individuals transition toward stability, accountability, and independent living.
A member of our team will review this referral and contact the referring provider regarding next steps, additional screening, or placement availability.