Wings of Hope Recovery LLC
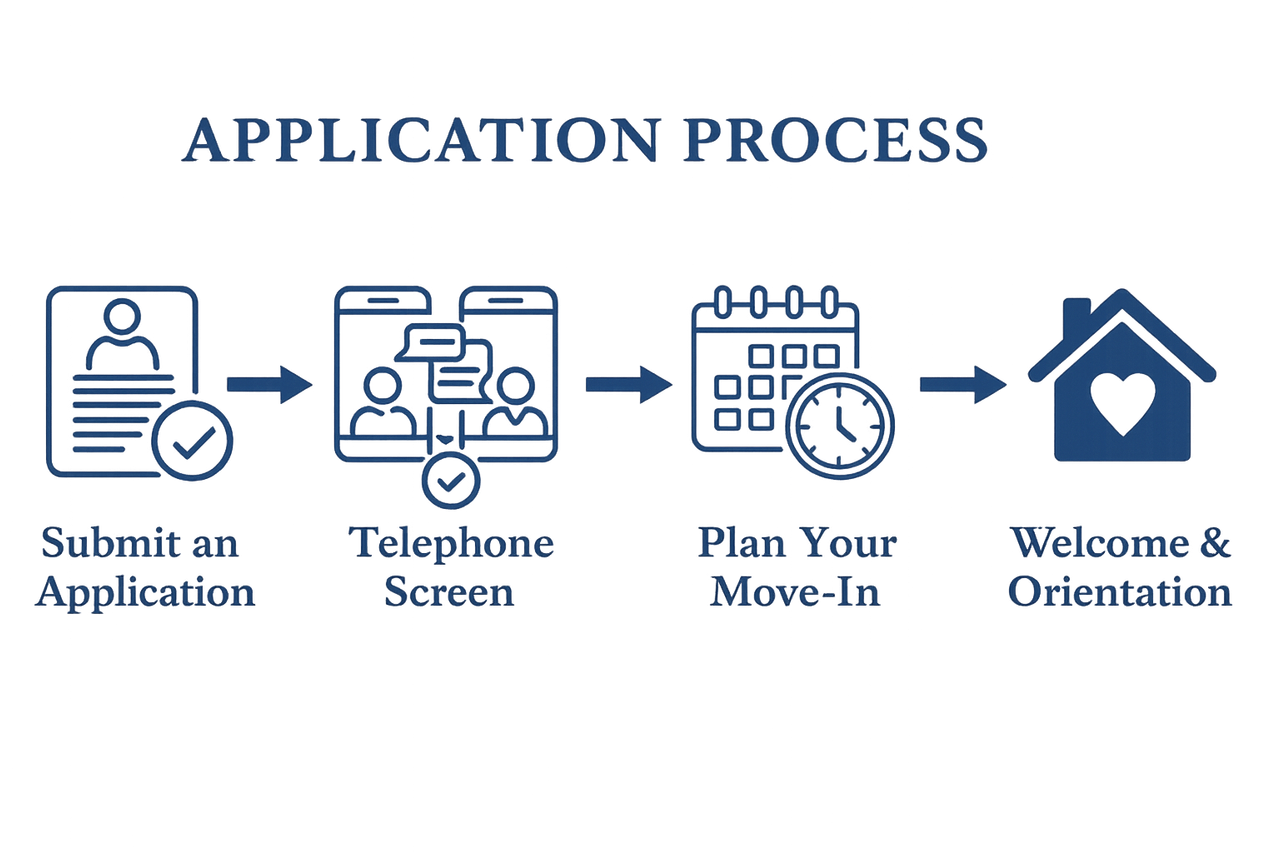
We welcome individuals who are ready to take the next step and become part of the Wings of Hope community.
Please complete this application as thoroughly and accurately as possible. Incomplete or false information may result in delays or denial of admission.
If you’ve already submitted an application and would like an update, give us a call at (860) 222-2768.
By submitting this application, I confirm that I am committed to maintaining my sobriety and contributing to a healthy, supportive living environment. I believe Wings of Hope can provide the structure and community I need to continue moving forward.
 General Information
Applicant (Person interested in moving into home)
Applicant's Name Client first nameClient middle nameClient last name
Applicant's Date of Birth Date
Applicant's Gender Client gender Client pronoun
Applicant's Address Client Address
City, State, ZIP Code Client CityClient StateClient Zip
Applicant's Phone Number Client phone
Applicant's Email Address Client email
Today's Date Date
Who is filling out this application?
Radio buttons
Name Text field
Phone Text field Ext Text field
Email Text field
Emergency Contact
Contact
How did you hear about us?
Dropdown
Referral Details
Name of Person Referring Text field
Role / Title Text field
Name of Organization Text field
Referring Person's Phone Text field Ext Text field
Referring Person's Email Text field
Recovery Background
Date of last use Date
Substance(s) of choice Client substances of choice
Do you have a sponsor or recovery support system? Client sponsor
Will you be able to submit a negative urinalysis (drug screen) upon entry? Dropdown
Treatment History
Are you currently in a treatment program? Dropdown
Expected Release / Completion Date Date
Were you in a program previously? Dropdown
Completion Date Date
Medical Information
Medications
List all medications you are currently taking (prescription and over-the-counter):
Medication
Health History
Indicate any history of physical health issues or diagnoses:
Client health problems
Indicate any history of mental health diagnoses:
Checkboxes
Medical / Diagnosis Notes (optional):
Paragraph
Insurance (used for IOP / treatment suggestions) Text field
Background Information
Criminal History
Is this a court-related or TPP referral? Radio buttons
Currently on Parole or Probation? Dropdown
Sex Offender Registry? Radio buttons
Have you ever been convicted of a crime? If yes, please provide details:
Paragraph
Is the applicant currently incarcerated?
Correctional Institute Text field
Estimated Release Date Date
Inmate # Text field
Financial Preparedness & Responsibility
Are you currently employed? Dropdown
Current / Most Recent Employer Text field
Position Text field Start Date Date
Additional Info:
Paragraph
Additional Information
Do you have reliable transportation? Radio buttons
Will you need a parking spot? Radio buttons
Do you need first-floor access, or are stairs okay? Dropdown
How long do you plan on staying with us? Client estimated length of stay
Desired move-in date Date
Anything else we should know? (contact preferences, placement considerations, etc.)
Paragraph
Agreement
I understand that my application will be reviewed and that admission into Wings of Hope Recovery is not guaranteed. I am fully committed to abiding by the rules and guidelines of the sober home, participating actively in the community, and maintaining my sobriety.
I understand that I am required to provide truthful, complete, and accurate information throughout the intake and admissions process. I acknowledge that any false, misleading, or incomplete information I provide—whether spoken or written—may result in denial of admission or immediate dismissal from the program.
Thank you for considering my application. I look forward to the possibility of joining the Wings of Hope community. Please feel free to contact us at (860) 222-2768 or admissions@wingsofhoperecovery.com if you have any questions or require additional information.
Agreed by:
[Your Signature]
Signature
Date
[Your Printed Name] Text field
By continuing, you agree that your electronic signature is the legally binding equivalent to your handwritten signature. Whenever you execute an electronic signature, it has the same validity and meaning as your handwritten signature. You will not, at any time in the future, repudiate the meaning of your electronic signature or claim that your electronic signature is not legally binding.
